- Home
- Health Technology
- Pulse oximeters: a useful estimate needs clinical context
Pulse oximeters: a useful estimate needs clinical context
Understanding home health technology

A fingertip device produces a percentage within seconds. That convenience is the appeal of pulse oximetry, but the display can make an estimate look more certain than it is. The useful question is what the reading means alongside symptoms, the person's condition and the purpose for which the device was designed.
Home monitoring is most helpful when it forms part of an agreed care plan. Before relying on a pulse oximeter, discuss whether it is appropriate, how to use it and what should trigger a call for help. A number without an action plan can create confusion as easily as reassurance.
What the device is estimating
The US Food and Drug Administration explains that pulse oximeters usually sit on a fingertip and use light to estimate blood oxygen saturation and pulse rate. They provide information without drawing a blood sample. Oxygen saturation and pulse rate are different measurements, even when they appear side by side.
The National Library of Medicine's MedlinePlus describes pulse oximetry as a quick, painless check used in settings from clinics to homes. It can help professionals assess people with conditions affecting oxygen levels or monitor treatment. It does not, by itself, identify which disease is causing a problem.
Think of the display as one observation in a wider clinical picture. An unexpected value might need a repeat measurement using the instructions, discussion with a professional or urgent assessment, depending on the circumstances. The device cannot choose among those responses for the person holding it.
Technique and the person both matter
FDA's consumer guidance advises following the manufacturer's instructions and the healthcare team's monitoring schedule. For a home reading, it recommends a warm, relaxed hand, keeping still and waiting for a steady result. Recording the value with the date and time can help a clinician interpret changes.
MedlinePlus lists factors that can affect accuracy, including dark nail polish, artificial nails, poor circulation, cold skin, tobacco use and darker skin pigmentation. It also notes that results may differ from the actual blood oxygen level and that a clinician may use an arterial blood gas test for a more accurate assessment.
These limitations should not become a reason to dismiss a person's symptoms. Nor should skin colour be treated as a simple correction that a user can add to a screen value. Graymedy's interpretation is that uncertainty belongs in the care decision, rather than being hidden behind a precise-looking percentage.
Check what kind of product you have
The FDA distinguishes devices intended for medical purposes from products marketed for general wellness, sport or aviation. Some medical-purpose oximeters are available over the counter after FDA clearance. General wellness products are not evaluated by the agency for clinical decision-making or deciding whether medical intervention is needed.
That distinction concerns the US regulatory framework; approval and market rules differ elsewhere. A marketplace description or familiar brand name is not a substitute for checking the product's intended use and the applicable local requirements. Ask a clinician or pharmacist if the label is unclear.
Performance across skin pigmentation remains a significant issue. FDA's public information describes concerns that readings can be less accurate in people with darker pigmentation. Its January 2025 guidance on improved testing was described as draft guidance in the material reviewed for this article; this explainer does not claim that the proposal has become a final standard.
Agree the response before the next reading
Ask the healthcare team which values or trends should prompt contact in your circumstances, and how symptoms should change that response. Baselines can vary with health conditions and altitude, so a general chart cannot replace a personal plan. Do not adjust prescribed oxygen or other treatment based on this article.
Serious or worsening symptoms need attention even when a display looks reassuring. Severe breathing difficulty or chest pain warrants urgent medical help; do not delay while repeatedly checking the device. FDA advises tracking how you feel as well as the readings and contacting a professional about concerning results.
For a monitoring review, bring the device instructions and a short record that connects readings with symptoms and circumstances. Ask the clinician to demonstrate how the equipment should be used and explain the response expected from you.
The practical promise of pulse oximetry is timely information. Its limit is that information still requires interpretation. Clear instructions, a suitable device and an agreed route to care make the reading more useful than an isolated number shared without context.
Sources: FDA: Pulse oximeters; MedlinePlus: Pulse oximetry; FDA: Pulse oximeter basics.
Editorial review: 20 October 2026. Educational explainer based on the cited sources; no original interviews or individual medical advice.
Image: Gustavo Fring / Pexels, used under the Pexels License. Illustrative stock photograph; no endorsement or individual diagnosis is implied.




Health Technology
View more
A prescription medicine increasingly arrives with a digital companion: a reminder, a symptom tracker or software linked to a delivery device. The FDA’s October 2026 final guidance gives drug companies a clearer route for deciding how those tools should be described and reviewed. The framework focuses on software distributed by, or on behalf of, a drug sponsor. It asks whether the content belongs in required labeling or promotional material, when the software should appear in prescribing information, and what the sponsor should submit. A feature is not yet a clinical benefit Device-connected software, such as an app paired with an inhaler, generally should be described in the medicine’s prescribing information. For standalone tools, the agency distinguishes convenience from a function essential to safe and effective use or supported by meaningful clinical benefit. That distinction matters for pharma’s digital-health strategy. Downloads, daily engagement and polished interfaces can describe product use. They do not, by themselves, establish that an app improves a health outcome. The practical question for developers Teams need to define the app’s intended role early, align its claims with evidence, and make the patient-facing instructions consistent with the medicine’s labeling. The final guidance also provides a decision tree and examples to help sponsors assess their software. For clinicians and patients, a reference on a drug label should still be read in context. Different functions serve different purposes; a reminder and a device-linked dosing tool do not carry the same responsibilities. The opportunity is better support around treatment, backed by a clear account of what has actually been demonstrated. FDA final guidance

Can a smartwatch flag high blood pressure before you know it?

Trial recruitment software faces a harder test: does it help people enrol?

After a stroke, wrist sensors could reveal recovery between clinic visits
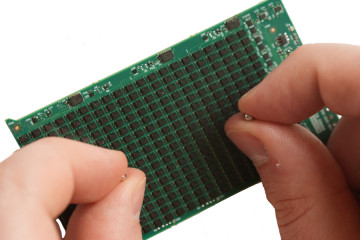
Controlling an artificial limb begins before the limb moves. A device must work out what its wearer wants to do, using signals that remain dependable as muscles contract, skin moves and activity changes. Researchers are now exploring whether a pair of tiny magnets can make that conversation clearer. A study published in Nature Sensors on 29 October describes an external sensor array that tracks magnetic beads inside human muscle. Led by Christopher Shallal and Cameron Taylor with senior author Hugh Herr, the work offers an early human test of an interface intended for future prosthetic control. Measuring movement beneath the skin The system, called MuSE, follows passive magnetic implants using sensors worn on the skin. The beads are about three millimetres across. Tracking their separation makes it possible to estimate how a muscle changes length and how quickly that change occurs. That is a mechanical measurement. Electromyography, the familiar alternative, records electrical activity associated with muscle activation. The two kinds of information are related, but they are not interchangeable. A control system benefits when the signal it receives closely represents the movement it needs to produce. The attraction is a wireless connection across the skin without a battery inside each bead. The experiment therefore concerns the quality of the interface as much as the sophistication of a robotic foot. An excellent motor cannot compensate reliably for an ambiguous instruction. Three participants, a carefully defined task The human study involved three people with below-knee amputations. All had undergone an agonist-antagonist myoneural interface procedure, which reconnects opposing muscles so they can retain a dynamic relationship. This specific surgical background matters when considering who the findings might eventually apply to. Participants also had implanted electrodes, enabling comparisons with both implanted and surface electrical measurements. In the reported experiments they used muscle signals to direct a cursor toward screen targets. They were not demonstrating improved walking with a prosthesis during those tests. MIT's account reports more accurate and stable control with the magnetic approach in that virtual task. It also says a larger study is evaluating actual prosthetic-limb control. The distinction prevents a promising measurement result from becoming an unsupported claim about fewer falls or better daily mobility. The researchers are extending an earlier idea Herr's group has investigated magnet-based muscle measurements for several years. Its earlier animal work established the possibility of tracking muscle length with implanted magnets. The new paper moves the question into human sensing with long-term implants, rather than introducing magnets to prosthetics for the first time. That progression is worth following because it makes the next question concrete. A laboratory demonstration must develop into a system that works while someone gets dressed, walks outside or changes position. Those are examples of future evaluation needs, not activities this small study has already validated. What a convincing next study would show Graymedy's interpretation is that future evidence should connect signal quality with outcomes that matter to users. Useful measures could include task success, effort, comfort and reliability across repeated sessions. A comparison should also specify which existing interface it seeks to improve upon. Safety needs equally explicit attention. Implanting an interface creates a different commitment from attaching a removable surface sensor. Longer follow-up and larger groups are needed to evaluate uncommon problems and practical maintenance. The small number of participants cannot answer every question about suitability. Generalisability is another issue. Results in people with this particular amputation procedure should not automatically be extended to every residual limb or to upper-limb use. Different anatomy, rehabilitation histories and goals could change what an effective interface requires. Readers can also ask how much calibration a future device would need and who would support it when circumstances change. These practical details belong in the evidence alongside laboratory accuracy, because an interface must remain useful between scheduled research visits. A useful advance without a finished product For people considering prosthetic options now, this paper is research to discuss, rather than evidence that a new commercial system is ready for routine use. Clinical choices still depend on the person's circumstances and the options their specialist team can actually provide. The wider significance is a change in what an artificial limb might listen to. Electrical activation indicates one part of muscle behaviour; direct mechanical tracking may supply another. Combining good engineering with careful clinical testing could make that extra information useful. The next milestone is showing that it improves life beyond the screen. Sources: Shallal and colleagues, Nature Sensors; Anne Trafton / MIT News, 29 October 2026; MIT's earlier magnet research. Photo: Courtesy of the researchers / MIT News, CC BY-NC-ND 3.0. Reviewed 5 November 2026. Independently written from public sources; no interview was conducted. General information, not individual medical advice.
A pacemaker designed to disappear after the heart recovers

Cochlear implants: the technology is only one part of hearing care
A new imaging AI study makes its answers easier to inspect

The promise of earlier warnings A hospital monitoring system may detect a subtle change in vital signs before it becomes obvious to a busy clinical team. Artificial intelligence can bring several measurements together, highlight patterns and suggest which patients deserve closer attention. Yet an alert is not a diagnosis. Its usefulness depends on whether the right person receives it, understands the evidence and can respond. The central question for digital health is not simply how accurately a model predicts deterioration, but how its output changes care. Prediction is not clinical certainty A risk score is usually based on information available at a particular moment: laboratory results, observations, medical history or notes. Some information may be delayed or missing. Patients also differ from those included in the training data. A model that performs well in one hospital could behave differently in another, especially when workflows, patient populations and equipment change. Clinicians therefore need to know what the system predicts, over what period, and which uncertainty remains. A warning about possible deterioration should support assessment rather than replace it. The cost of too many alerts A tool that sends repeated warnings can create fatigue, even if each individual notification seems defensible. Staff must weigh alerts against examinations, medicine rounds and competing emergencies. If a system flags too many patients who do not deteriorate, confidence can fade. If it sets its threshold too high, important cases may be missed. Healthcare organizations should evaluate both false alarms and missed events, alongside how often teams have enough time and resources to act on a meaningful warning. Designing a workable response A useful deployment defines responsibility in advance. Who receives an alert first? Is there an escalation pathway? What happens at night or when the assigned clinician is unavailable? Can staff review the trend and record why they accepted or dismissed the recommendation? Without clear answers, a sophisticated algorithm may add noise rather than improve outcomes. Human factors such as screen design, timing and the availability of a rapid-response team deserve the same attention as statistical performance. Fairness and changing conditions Age, disability, access to testing and differences in medical documentation can influence the data a model sees. Evaluations should examine whether errors concentrate in particular patient groups rather than rely only on a single overall accuracy figure. Systems also require monitoring after launch. Changes in clinical practice, disease patterns or electronic records can alter their performance. An AI model is not a device that can be installed once and assumed to remain dependable indefinitely. What evidence should buyers request? Before purchasing an alert platform, a hospital can ask whether it has been tested prospectively in comparable settings and whether the evaluation measured patient-relevant outcomes. Measures such as alert counts and prediction accuracy matter, but so do response time, avoidable harm, workload and unintended consequences. Procurement teams should request information about data privacy, cybersecurity, updates, clinician training and the process for reporting failures. External validation is particularly valuable when marketing claims are based on a single institution. Keeping patients in the conversation Patients may reasonably want to know whether software influences their care and how clinicians interpret its suggestions. Transparent communication need not involve a technical explanation of every model feature. It can describe the technology's supporting role, the continuing responsibility of the medical team and the safeguards available when recommendations are questioned. Meaningful oversight also includes a mechanism for patients and staff to report concerns about an automated decision. The measure of success The most promising clinical AI products will not necessarily generate the greatest number of predictions. They will help teams recognize actionable problems while preserving judgment, accountability and trust. Responsible adoption means starting with a clear clinical need, testing in real workflows, auditing performance and adjusting or retiring tools when evidence warrants it. In medicine, a timely warning is valuable only when it leads to a safer, more informed response. Questions for implementation teams Successful implementation also requires an agreed process for pausing a system when performance becomes concerning. Hospitals can decide in advance which indicators trigger review, how overrides are documented and which multidisciplinary committee owns oversight. Clinicians should have a straightforward way to flag a misleading notification without fearing that questioning software will be treated as noncompliance. Staff training is most useful when it includes realistic examples of false alarms, uncertain predictions and patient circumstances the model may not recognize. These operational details can appear mundane beside the excitement around algorithms, but they determine whether technology earns a durable place in patient care.

A speech clock explores links between ageing and dementia
A second look at sleep-study heart signals could reveal longer-term risk