- Home
- Health Science
- See the target, then test the treatment: the promise of antibody-guided cancer imaging
See the target, then test the treatment: the promise of antibody-guided cancer imaging
Cancer imaging • The science behind theranostics
GRAYMEDY EXPLAINER · Reviewed October 17, 2026
A cancer scan can show where a suspicious mass sits. A more ambitious question is whether imaging can reveal the biology that makes a treatment worth trying—and show where that treatment travels after it enters the body. Antibody-guided imaging sits at that intersection of molecular biology, measurement and clinical decision-making.
This explainer was prompted by City of Hope’s March 10, 2026 interview with Anna Wu, Ph.D., hosted by Monty Pal, M.D. In the conversation, Wu describes engineered antibody fragments, CEA-directed research, a planned copper-64 PSCA imaging study in pancreatic cancer, and imaging of CD8 immune cells. Those program descriptions reflect the interview’s date; they are not presented here as confirmed October recruitment updates. Read City of Hope’s episode and transcript.
The key distinction: seeing a biological target, delivering radiation to it and improving a patient’s outcome are separate achievements. Each needs its own evidence.
1. Turning a targeting molecule into a measurable signal
Antibodies recognize particular molecular features. Researchers can adapt them into probes that carry a detectable label. The broader field includes radioactive, optical, magnetic-resonance and ultrasound approaches; antibody fragments give researchers additional formats to optimize for a particular imaging task. The scientific challenge is to preserve useful binding while producing a signal that can be distinguished from background. Freise and Wu’s review of antibody imaging explains this engineering framework.
For a reader, the practical question is: what does this particular probe measure? A signal associated with a tumor target answers a different question from a probe associated with immune cells. Neither should be interpreted simply as a universal picture of “how much cancer” is present.
2. What theranostics adds
Theranostics links a diagnostic approach with a treatment directed at the same biological target. A radiopharmaceutical can combine a targeting molecule, a radioactive component and the chemistry connecting them. Imaging can help establish whether an agent reaches a lesion; a related therapeutic version can carry radiation intended to damage cancer cells. The National Cancer Institute describes how imaging compounds have provided starting points for treatment development. NCI’s molecular radiation therapy explainer.
This approach offers a way to ask about delivery before relying on a treatment’s presumed selectivity. But a useful image is not itself proof of a safe therapeutic dose. Researchers still need to determine exposure in normal organs, how long the compound remains in the body and whether the balance of benefit and harm is acceptable.
Graymedy’s reading: the most valuable promise is better-informed testing. A visible target can narrow a hypothesis; clinical trials must establish whether acting on it helps.
3. A concrete example: imaging CEA-positive cancers
A City of Hope study registered as NCT02293954 evaluates copper-64-labeled anti-CEA antibody M5A for PET imaging. One listed aim is to determine its ability to localize CEA-positive cancers, including several gastrointestinal and other tumor types. This illustrates an imaging question: does a labeled antibody find the intended disease sites in people? Read the clinical trial record.
A registry entry describes a study’s objectives and design. It should not be read as a positive result. Likewise, evidence for one antibody, radioactive label or cancer population does not automatically transfer to another. Readers considering a research study should use its current record and the study team to establish eligibility and availability.
4. Imaging the immune response: what the 2026 evidence says
CD8 PET takes a different angle: it measures a signal associated with CD8 immune cells rather than simply targeting a tumor-associated protein. The prospective, multicenter phase II iCorrelate study examined the relationship between PET measurements using zirconium-89 berdoxam-crefmirlimab and CD8 cells measured in core-needle biopsies in people with solid tumors receiving immune checkpoint blockade.
Published March 27, 2026, the study reported 49 patients and 70 biopsies used for correlation. Mean uptake in the biopsied tumor, normalized to the aorta, correlated with biopsy immunohistochemistry at 0.49 (95% confidence interval 0.26–0.59). That is a moderate association rather than a perfect match. Read the phase II iCorrelate paper.
What this establishes: evidence that the imaging measurement relates to a tissue-based CD8 measurement. What this statistic does not establish: that using the scan to choose or change therapy improves survival, quality of life or treatment safety. An association with a biological marker and clinical utility are different endpoints.
Earlier first-in-human work included an initial six-patient dose-escalation cohort and assessed pharmacokinetics, distribution and lesion targeting. That sequence shows why development proceeds through measurement and safety questions before broader claims. Read the early anti-CD8 minibody study.
5. An established treatment category, with investigational branches
Targeted radionuclide therapy is already used for selected patients with advanced prostate cancer and gastroenteropancreatic neuroendocrine tumors, as described in NCI’s radiation therapy overview. That clinical footing should be distinguished from experimental antibody platforms discussed in research interviews.
The phrase “theranostics” therefore needs a second question: which agent, for which disease and under which evidence or authorization? A broad technology category cannot tell a patient whether a particular option is appropriate or available.
Questions to bring to the next breakthrough headline
- What is being measured? Tumor-associated target, immune-cell distribution or another process?
- What was actually tested? Laboratory feasibility, human safety, agreement with biopsy or a treatment outcome?
- What is the comparison? A new measurement needs a defined reference and an explanation of disagreement.
- What decision would change? Ask whether evidence supports using the result to guide care.
- What is the date? A planned study in an interview is not a current enrollment announcement.
Sources, attribution and image credit
Originating source: City of Hope, How engineered antibodies and next-generation imaging tools are reshaping cancer care with Anna Wu, Ph.D., March 10, 2026; host Monty Pal, M.D. Watch the original video. This is independently structured Graymedy explanatory writing, supported by the linked primary research, registry and NCI resources. No interview was conducted by Graymedy.
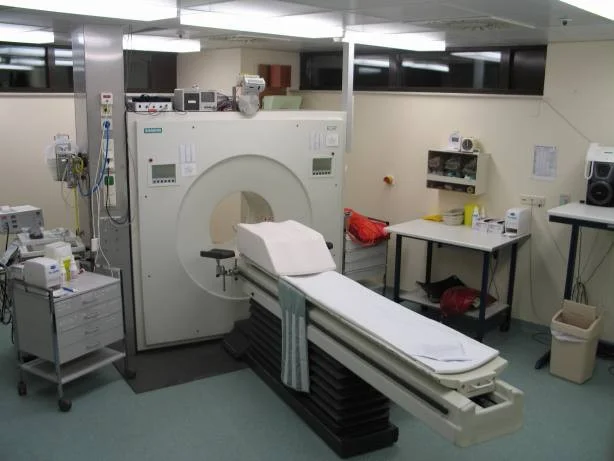
Photo: Jens Maus / Wikimedia Commons, public domain.
Scope: educational reporting reviewed October 17, 2026. This article explains research and evidence; it does not establish individual treatment suitability or confirm current trial recruitment.




Health Science
View more
A new environmental-health finding is more specific than a broad claim that a chemical causes breast cancer. NIH researchers reported an association between two legacy PFAS and estrogen receptor-negative breast cancer, while finding no clear association with breast cancer overall. The finding behind the headline NIH’s November 5, 2026 report describes research from the Sister Study. Investigators measured 17 PFAS in blood collected before diagnosis, comparing 1,609 women who developed breast cancer with a comparison sample of 2,269 women. Participants had a sister with a previous breast-cancer diagnosis. Women in the highest PFOA group had a 67% higher rate of ER-negative breast cancer than those in the lowest group. For PFOS, the relative difference was 93%. These are comparisons between exposure groups, not an individual woman’s absolute probability of developing cancer. What it does not show An observational association does not, by itself, establish causation. The analysis also does not show that every PFAS has the same relationship with cancer. The authors called for research on newer replacement compounds and on populations with higher exposures. For readers, three questions help keep the result in proportion: which exposure was measured, which outcome was associated with it, and which people were studied? Replacing those details with a general claim can make an informative finding misleading. Keeping uncertainty useful Graymedy’s interpretation is that a specific signal is a reason for further investigation, not a reason to assign blame for an individual diagnosis. Environmental-health evidence is most useful when it helps define the next study and supports clear public communication. It should also be possible to discuss uncertainty without dismissing the concern. Replication, better exposure measurement and examination of potential mechanisms can strengthen or revise the picture. The appropriate response to this paper is careful attention rather than a promise of a new screening test or treatment. Sources NIH research report, November 5, 2026; Chang et al., Journal of Clinical Oncology. Editorial review: November 9, 2026. Independent research analysis; not individualized risk assessment. Image: National Cancer Institute, ID 2175, archival breast-cancer cell micrograph, 1985. Public domain. Image source. Not a Sister Study specimen or PFAS experiment.
Depression research finds a possible bottleneck in the brain’s memory centre
Can changing scarred tissue help cancer immunotherapy work better?
Christopher Rodell is testing whether a gel can teach the immune system to accept new beta cells
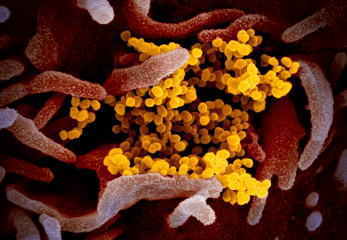
A virus’s genetic material is often pictured as a set of instructions waiting to be copied. New coronavirus research suggests a more active role: particular stretches of RNA help organise contacts with viral proteins, and disrupting those contacts can interfere with replication. That makes the meeting points themselves interesting places to look for future medicines. A study highlighted by UC Riverside on 30 October and UC San Diego on 2 November 2026 maps these interactions across SARS-CoV-2. The experiments identify biological vulnerabilities in cultured cells. They do not announce an antiviral ready for patients or establish protection against a future pandemic. Reading the genome as a working structure RNA can carry genetic information, but it also has structural and regulatory functions. The National Human Genome Research Institute describes several forms of RNA with different cellular jobs and notes that some viruses use it as their genome. A sequence can therefore be both information and part of an operating mechanism. This study examines that second possibility in the coronavirus life cycle. Instead of looking only at a protein as an isolated target, the researchers asked where proteins contact the viral RNA. The resulting map offers a way to study how those contacts influence the virus’s activity. The shift is useful because a genome’s sequence alone does not explain everything it does. Knowing the letters is different from understanding which molecular partners use them, when those partners bind and what happens if access is blocked. Finding contacts, then testing their importance The team used enhanced cross-linking and immunoprecipitation, usually called eCLIP, to survey interactions involving three viral proteins: NSP8, NSP12 and nucleocapsid, or N. The approach looked across the genome rather than limiting the search to sites already expected to be important. UC San Diego’s account describes an interaction between N and a region near the genome’s beginning, the 5′ untranslated region, with a role in protein production. It also describes a previously unrecognised interaction between NSP12 and RNA encoding another viral protein, NSP3. These findings give researchers more specific functions to investigate. A binding map is a starting point. The stronger question is whether interfering with a contact changes what the virus can do. This is where the study moves from description towards a functional test. Blocking a meeting point The investigators used short, modified nucleic-acid sequences designed to bind selected RNA regions and obstruct their interactions. Blocking the sites reduced viral replication in Vero cells, which originate from African green monkey kidney cells. Similar effects were observed in human lung cells. Those are cell-culture experiments. UC Riverside explicitly reports that animal work is still needed to determine whether the findings could translate into a therapeutic approach. Human cells in a laboratory are biologically informative, but they do not reproduce an entire person’s infection, immune response or drug exposure. The distinction matters for the next stage of research. A candidate would need to reach the relevant cells, remain active there and avoid unacceptable effects. Identifying a vulnerable interaction and delivering an effective treatment against it are connected but separate achievements. Could the approach outlast viral change? The researchers are interested in contacts involving machinery or sequences shared among coronaviruses. If an interaction is essential and difficult for a virus to alter, it could be a more durable target. That is the rationale for broader antiviral development, rather than evidence that resistance has already been overcome. Graymedy’s interpretation is that breadth should be tested directly. A promising result against one virus cannot establish the same effect against a related virus, and similar sequences do not guarantee identical biological behaviour. Studies across viruses and experimental settings would help define the actual reach of the idea. The same care applies to comparisons with existing medicines. Current antivirals already target essential viral processes. This work adds possible points of intervention; it does not show that a new approach is safer or more effective than treatments used today. Why this map is worth following The contribution is a more detailed view of how viral components cooperate. It produces testable questions about regulation, replication and vulnerability, giving later drug-development work something more precise than a broad instruction to attack the virus. Its importance will grow if those questions lead to reproducible effects in more realistic models and eventually useful clinical candidates. For now, the breakthrough being pursued is an understanding of viral machinery that could widen future treatment options, with the distance to patient benefit kept visible. Sources: UC San Diego: research report, 2 November 2026; UC Riverside: methods and limitations, 30 October 2026; Study record: genome-scale eCLIP mapping, Nature Communications; NHGRI: RNA and its functions. Micrograph: NIAID-RML / Wikimedia Commons, CC BY 2.0; resized. Reviewed 4 November 2026. Independently written from public sources; no interview was conducted. General information, not individual medical advice.
Transplant research looks at the drainage system around the immune response
A new colorectal cancer atlas looks beyond the under-50 divide

Why Replication Matters More Than a Single Breakthrough Study
Some cells stop dividing without disappearing. They remain biologically active, sending signals into surrounding tissue. This state, called cellular senescence, has become a major focus of ageing research because it can help protect the body in some circumstances and contribute to damage in others. The challenge is telling those situations apart. Researchers need to know which cells have become senescent, where they sit, and what they are doing before they can design treatments that target them accurately. A growing effort to map these cells is making that question more concrete. Why a stopped cell can still matter Senescence is a response to stresses such as DNA damage or disrupted cell function. Stopping a damaged cell from multiplying can provide an important safeguard against cancer. Senescent cells also participate in normal processes, including tissue repair. Their presence alone therefore does not automatically mean disease. Problems can emerge when these cells persist and release substances that alter their surroundings. Scientists call this mixture the senescence-associated secretory phenotype, or SASP. Its components can influence inflammation, neighbouring cells and tissue maintenance. The effects depend on the biological setting, which makes the familiar description of senescent cells as simply harmful incomplete. A SenNet Consortium perspective in Nature Aging explains why cell identity, the trigger for senescence and the tissue environment all matter. A single measurement cannot capture that complexity across the whole body. A map built around cellular differences In June 2026, the US National Institutes of Health reported a collection of studies advancing the Cellular Senescence Network, known as SenNet. The research introduces a framework of “senotypes”: patterns that distinguish senescent cells according to their context and characteristics. The work includes mapping in tissues such as the lungs, lymph nodes and the brain’s prefrontal cortex, alongside methods for detecting rare cells within complicated tissue samples. Combining molecular measurements with information about location helps researchers investigate how cells interact with their immediate neighbourhood. As the NIH announcement makes clear, this is groundwork for more selective therapies. An atlas can help researchers identify promising targets; it does not itself establish that a treatment prevents age-related illness. What blood measurements may reveal A related NIH research summary describes a tool called the Senescence Catalog, or SenCat, built from gene activity and protein measurements in 14 types of human senescent cells. The findings reinforce that senescence has several molecular forms rather than one universal signature. In companion research, investigators measured associated blood proteins in more than 2,000 people from two long-term ageing studies. Some patterns were linked to health characteristics including kidney disease, walking pace and diabetes. Cell-specific signals also appeared relevant: markers connected with kidney-cell senescence were associated with kidney disease. These reported associations make the proteins useful research leads. They do not show that a commercial blood test can reliably guide an individual’s treatment, or that changing a marker will necessarily improve health. Why removing every senescent cell is not the goal Experimental medicines called senolytics aim to eliminate selected senescent cells. Animal research has encouraged interest in this approach, but translating it into useful care requires a careful balance. The same broad cellular process can contribute to disease while also supporting healing and limiting uncontrolled growth. The NIH Intramural Research Program describes efforts to find molecular markers that distinguish relevant cells and measure whether interventions affect them. Identifying a target, reaching it safely and demonstrating meaningful benefit are separate tasks. Results in mice cannot establish that an intervention will extend healthy life in people. Future clinical studies will need to establish who benefits, which conditions should be treated and how outcomes change over time. Tracking side effects will be as necessary as measuring changes in cell numbers or blood proteins. What progress should look like SenNet’s public programme is designed to share maps, methods and common definitions so that laboratories can compare results. That infrastructure matters because inconsistent ways of identifying senescent cells can make apparently similar studies difficult to interpret. For readers, the useful questions are specific: which cells were studied, in what tissue, and was the evidence obtained from laboratory models or people? A credible treatment claim must also show a measurable health benefit and an acceptable safety profile. The promise of this research lies in understanding cellular ageing precisely enough to intervene wisely, while preserving the functions that help keep tissues healthy.

Sleep and the Brain’s Waste-Clearance System: What Human Studies Reveal

Your Body Has Multiple Clocks: How Circadian Rhythms Shape Sleep and Metabolic Health