A new home for armed CAR-T: what the Lakefront deal means for cancer research
Cell therapy • Research and deal analysis

GRAYMEDY EXPLAINER · Reviewed October 17, 2026
A change of ownership can keep a scientific idea alive. It cannot answer whether that idea will help patients. That distinction is central to the sale of Lakefront Biotherapeutics’ early-stage cancer cell-therapy portfolio to Armed Cell Therapeutics, a Belgian biotechnology company.
The transaction gives experimental programs a route forward after their former owner stepped back from the field. For readers following cancer innovation, the useful questions now concern the experiments, clinical plans and evidence that come next.
The key distinction: These are preclinical research programs. A completed acquisition is a business milestone, not proof of safety, effectiveness or regulatory approval.
What changed hands?
In its October 14 announcement, Lakefront said it had completed the sale of its early-stage cell-therapy pipeline. The technology originated with AboundBio, which the company acquired in 2022 when it was known as Galapagos.
The disclosed terms include €8 million upfront, eligibility for up to $230 million in milestone payments, and a low-single-digit royalty. The euro and dollar amounts are reported in their original currencies. The milestones are contingent; they should not be treated as money already paid or a guaranteed valuation.
Lakefront also said the wind-down of its legacy cell-therapy activities was substantially complete. It now describes its clinical portfolio as focused on immunology and inflammation, anchored by the BCMA×CD3 T-cell engager gamgertamig for autoimmune diseases.
What does “armed” CAR-T mean?
CAR-T stands for chimeric antigen receptor T-cell therapy. As the National Cancer Institute explains, immune cells can be modified in a laboratory to produce receptors that recognize particular proteins on cancer cells. The cells are expanded and returned to the patient to attack cells carrying the target.
Armed Cell’s acquisition announcement describes constructs using fully human binders and additional human-protein payloads. The design combines recognition of multiple targets with extra biological functions intended to sustain anti-tumor activity. These are engineering goals, not clinical findings.
The buyer identifies non-Hodgkin lymphoma and small cell lung cancer as the two lead disease settings. Its stated aim is to address problems such as relapse, inadequate persistence of therapeutic cells and resistance within tumors. It says a research team in the United States and Europe is advancing the work toward clinical testing.
Why the cancer setting matters
Blood cancers and solid tumors pose different challenges. NCI’s overview of CAR T-cell research describes established benefits in certain blood cancers, while explaining why solid tumors have been harder to treat with this approach.
A useful target must help distinguish cancer from healthy tissue. Within a solid tumor, different cells may carry different amounts of the target—or lack it entirely. Surrounding biological signals can also suppress immune-cell function or keep therapeutic cells from reaching the cancer.
That is the rationale for studying approaches that recognize more than one target or carry additional functions. It does not establish that a particular design solves these problems. Evidence from one cancer type also cannot be assumed to apply to another.
Safety remains part of the same question. NCI notes that CAR-T therapy can cause cytokine release syndrome, which can sometimes be severe, and can damage normal cells that share a recognized target. More biological activity is therefore not automatically a better treatment.
A familiar team, with a dated leadership detail
Jonathan Gardner’s October 15 report for BioPharma Dive, which prompted this article, places the deal in the context of Galapagos’ earlier move into cell therapy and subsequent retreat. It reports that former Galapagos executive Willemijn Kremer will become Armed Cell’s CEO, succeeding Paul Stoffels in that role, while Stoffels chairs the company.
The buyer’s October 14 acquisition release still lists Stoffels as interim CEO and chair, alongside chief scientific officer John Mellors and board member Peter Verhaeghe. We identify the dates and sources because the documents describe different points in the leadership transition.
Graymedy’s reading: continuity creates an opportunity to test
Our analysis: The immediate significance is organizational. A specialist owner can make a research program its central priority. That can be valuable, but ownership and experience are inputs to development. Neither substitutes for a reproducible manufacturing process, a credible clinical study or transparent results.
The most informative next announcement would connect the scientific proposal to a testable plan. Readers should look for a defined candidate, a specified patient group and a clear account of what investigators intend to measure. A statement that a program is moving toward the clinic leaves important questions open.
Similarly, a large potential milestone figure says little about the probability of clinical success. It describes a contract’s possible future payments. Treating it as evidence that the therapy works would mix financial terms with medical evidence.
What to watch next
- Candidate disclosure: Which targets and payloads are being tested, and what evidence supports the combination?
- Clinical entry: Has a study actually opened, where is it registered, and which patients are eligible?
- Safety and feasibility: Can the cells be manufactured consistently and administered at a tolerable dose?
- Meaningful outcomes: How many patients were treated, how were responses defined, and how long did they last?
- Comparability: Do later data support an advantage over the care available to the same patient population?
These are questions for future disclosures, not results established by this acquisition. Until clinical evidence is available, the most accurate description is an early research effort with a new path forward.
Sources, attribution and editorial note
This original Graymedy explainer was prompted by Jonathan Gardner’s Belgian startup revives Galapagos CAR-T research, published by BioPharma Dive on October 15, 2026. Transaction details were checked against Lakefront’s October 14 release; program descriptions against Armed Cell’s October 14 acquisition release. NCI’s educational resources provide the general CAR-T background. All are linked above.
Company descriptions of intended performance remain claims to be tested. Graymedy’s interpretation is labeled as analysis. This article does not report new clinical results and is intended for general information, not individual treatment advice.
Photo: Rhoda Baer / NIAMS.



Medicines
View more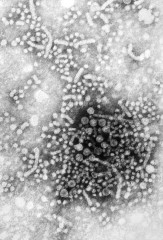
A limited course of treatment is becoming a practical possibility for some people with chronic hepatitis B. The FDA’s October 20 approval of Hibsago (bepirovirsen) adds an antisense medicine to existing antiviral therapy for carefully selected adults. The advance is meaningful, but it does not mean every patient can stop long-term treatment. In two trials, 24% of Hibsago recipients met the criteria to discontinue their existing antiviral, compared with none receiving placebo. At 24 weeks after stopping all hepatitis B treatment, 19% of Hibsago recipients retained viral control with undetectable hepatitis B surface antigen. Selection comes before treatment The US indication covers adults without cirrhosis who have received nucleos(t)ide analogue therapy for at least six months, have suppressed HBV DNA, and have surface antigen levels no higher than 3,000 IU/mL on an FDA-authorized test. Bepirovirsen targets viral RNA, reducing production of viral proteins as well as supporting suppression of the virus. Hibsago is given for up to 24 weeks alongside the existing antiviral. That background therapy continues for at least another 24 weeks. Any later withdrawal depends on the clinician’s assessment and laboratory criteria; it is not an automatic next step. The follow-up is part of the medicine The prescribing information carries boxed warnings for liver flares and potentially life-threatening reductions in platelets. Kidney function and inflammatory reactions also require attention. Laboratory testing before, during and after treatment is central to safe use. HBV can worsen after antiviral discontinuation, so continued follow-up matters even when treatment has ended. For pharma, the broader signal is a move toward finite regimens tied to biomarkers and a defined monitoring pathway. For patients, the immediate question is narrower: whether their disease profile and access to follow-up make this option appropriate. FDA approval · Prescribing information Image: CDC / Betty Partin, PHIL.
Ultomiris reaches IgA nephropathy—with a kidney-outcome question still open
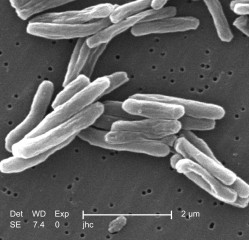
For shorter TB treatment, a drug must reach the bacteria’s hiding place
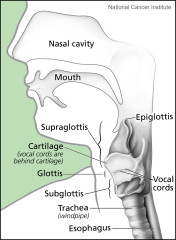
A new head-and-neck cancer approval brings an option—and an evidence question
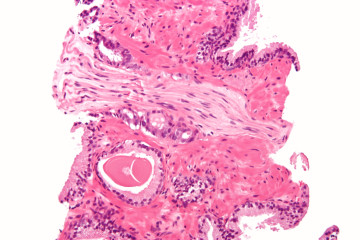
A new cancer-drug indication can change the timing of a treatment discussion. It can also make a laboratory result more consequential. The latest U.S. approval for talazoparib brings those changes together for a genetically defined group of people with metastatic prostate cancer. On 26 October, the FDA approved talazoparib, sold as Talzenna, with enzalutamide for adults whose metastatic prostate cancer is androgen pathway modulation-naïve or sensitive and has a qualifying homologous recombination repair gene mutation. An FDA-authorized test must establish that molecular eligibility. The decision is specific, rather than a recommendation for everyone with prostate cancer. The genetic result is part of the treatment Homologous recombination repair, usually shortened to HRR, helps cells repair DNA damage. Alterations in this pathway provide the rationale for studying a PARP inhibitor such as talazoparib. Enzalutamide acts through androgen-receptor signalling. The combination brings two different biological approaches into the same regimen. For patients, the practical starting point is a precise explanation of their result: which alteration was found, which test detected it and whether it matches the approved indication. A headline about a targeted treatment does not establish eligibility. Nor can a tissue photograph reveal the molecular information required for selection. What Neeraj Agarwal and colleagues tested TALAPRO-3, reported by Neeraj Agarwal and colleagues in the New England Journal of Medicine, randomly assigned 599 patients to talazoparib plus enzalutamide or placebo plus enzalutamide. Participants also received androgen-deprivation therapy. It was a double-blind phase 3 trial funded by Pfizer. At three years, the estimated proportion alive without imaging-based progression was 77% with talazoparib and 56% with placebo. That 21-percentage-point difference gives an absolute view of the finding. The reported hazard ratio for progression or death was 0.48. The endpoint combines progression detected on imaging with death. It is not a measure of the proportion cured, and a hazard ratio is not a personal forecast. The result supports a treatment option in the population studied, with benefits that still have to be weighed against harms. A survival claim would go beyond the evidence The FDA says overall-survival data were immature when the progression analysis was performed. Delaying progression is meaningful, but it should not be presented as a proven extension of life in this earlier treatment setting. Further follow-up addresses a different and important question. This distinction also helps readers interpret promotional language. Pfizer's earlier trial announcement emphasised the relative reduction in progression or death. That description refers to the trial endpoint and comparison; it does not mean the medicine halves every participant's chance of dying. The monitoring burden belongs beside the benefit The trial report found serious adverse events in 42% of the talazoparib group and 32% of the control group. Severe anaemia was a prominent problem. The current prescribing information describes substantial rates of dose interruption and reduction in TALAPRO-3, showing that an oral regimen can still require intensive management. The label warns about myelosuppression and myelodysplastic syndrome or acute myeloid leukaemia, among other risks. Blood-count monitoring and clinical review are therefore central to treatment. The dosing information also includes adjustments for particular circumstances; patients should not change doses themselves. These are reasons for an individual discussion about fitness, other medicines, existing blood problems and the support needed during therapy. Convenience matters, but taking a medicine at home does not remove the need for a specialist team or a plan for reporting symptoms. Keeping a written record of the testing result and the proposed monitoring schedule may help patients follow that discussion and share it with the professionals involved in their care. Questions for the next appointment Graymedy's reading is that the most useful consequence of this approval is a more specific consultation. A patient can ask whether molecular testing is complete, why this combination is being considered now, what alternative regimens are relevant and which outcomes the team hopes to improve. It is also reasonable to ask how often blood tests and visits will be needed, what would trigger a treatment pause and how costs or access are handled locally. The FDA decision concerns the United States. The agency's announcement said collaborating Australian and Canadian reviews were ongoing at that point; it did not establish worldwide availability. Agarwal and colleagues' work strengthens the evidence for earlier, genetically selected treatment. Its value is clearest when the test result, progression benefit, remaining survival uncertainty and monitoring requirements are discussed together. That is a more useful update than treating approval as the end of the clinical conversation. Sources: FDA approval, 26 October 2026; TALAPRO-3 trial report; Current Talzenna prescribing information; Pfizer's May trial announcement. Photo: Nephron / Wikimedia Commons, CC BY-SA 3.0; resized. Reviewed 5 November 2026. Independently written from public sources; no interview was conducted. General information, not individual medical advice.
Sixteen bacterial strains, one clinical question: can SER-155 prevent bloodstream infections?
Allopurinol for gout: treating the urate level between attacks
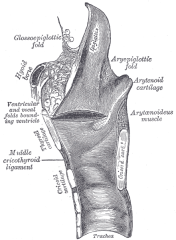
Voceryq gains FDA approval to reduce repeat surgery for a rare airway disease

A growing treatment puzzle People living with several long-term conditions may receive medicines from different specialists, urgent-care services and primary-care teams. Each prescription may have been reasonable when introduced, yet the combined regimen can become difficult to manage. Interactions, overlapping treatments, changing kidney function and complex schedules can alter the balance between benefit and harm. A structured medication review looks at the whole person, rather than judging each medicine in isolation. What polypharmacy means Polypharmacy commonly describes the use of multiple medicines, but the number alone does not establish a problem. Several treatments may be essential for someone with complex disease. The more useful question is whether every medicine still has an appropriate indication and whether the overall plan matches current health needs. Reviews should consider prescribed tablets, over-the-counter remedies, vitamins and herbal products because patients may not think to mention everything they take. How a review begins Clinicians first need an accurate list: medicine name, dose, timing, purpose and actual use. The patient's account is crucial. Someone may skip an afternoon dose because of work, halve a tablet after dizziness or continue a medicine that was supposed to stop. A nonjudgmental conversation can reveal such differences. Pharmacy dispensing records, hospital summaries and medicine containers can help, but none replaces asking what happens in daily life. Benefits, burdens and changing priorities A medicine that prevents a future complication may be worthwhile for many years, while another offers little benefit once circumstances change. Some treatments require monitoring, have cumulative adverse effects or are difficult to swallow. Older adults may be especially vulnerable to certain sedating and anticholinergic medicines, although risk depends on the individual and the product. Decisions must account for goals such as symptom relief, independence and avoiding hospital visits, not merely laboratory targets. Deprescribing is a clinical process Deprescribing means supervised reduction or withdrawal when potential harms exceed expected benefits. It does not mean abruptly stopping treatment or assuming fewer medicines are always safer. Some medicines require gradual tapering and monitoring because sudden withdrawal can cause rebound symptoms or serious complications. A clinician may change one treatment at a time, agree on what to monitor and schedule reassessment. Patients should not stop prescribed medicines solely because they read about polypharmacy. Communication across specialties Medication decisions can be complicated when one specialist adds a drug without knowing what another has prescribed. Shared records are helpful but may not capture every pharmacy or over-the-counter purchase. A designated clinician or pharmacist can coordinate the list and communicate changes across teams. When a medicine is stopped, documenting why helps prevent it from being restarted inadvertently during the next hospitalization. Clear explanations also reduce confusion when packaging or brand names change. The patient perspective Side effects do not always appear on a laboratory report. Fatigue, falls, dry mouth, nausea, sleep disturbance and the cost of monthly refills may matter greatly. Patients should feel able to describe these effects and ask why a medicine is necessary, how long it is expected to continue and which alternatives exist. A useful review discusses risks plainly and respects a person's preferences, while recognizing that choices may require compromise between competing health goals. Making reviews routine Medication reconciliation is especially useful after hospital discharge, following a new diagnosis or when a regimen becomes hard to manage. Ongoing reviews can prevent small discrepancies from accumulating over time. The outcome should be a current list, a rationale for each important change, any monitoring arrangements and a clear contact for questions. Safer prescribing is not simply about adding the latest treatment; sometimes the most thoughtful intervention is to review what is already there. What a useful medication plan looks like At the end of a review, the patient should ideally have a clearly dated medication list and understand the intended purpose of each treatment. Changes should identify what to start, continue, adjust or stop, with written instructions when tapering is necessary. The team may also explain which symptoms warrant urgent attention and which routine checks are needed to judge whether a change is working. Where multiple professionals are involved, the updated plan should be shared with those responsible for ongoing prescriptions. That creates a practical bridge between an informed discussion and safer daily medicine use.

GLP-1 Medicines Beyond Weight Loss: What Heart and Kidney Benefits Really Mean
Naloxone works best when people have an emergency plan